A lot of people put off seeing a pain specialist because they don’t know what the visit involves. Some expect to be handed a prescription and sent home. Others worry they’ll be pushed toward a needle before anyone has listened to them. Neither is how a good first appointment should go.
The first visit is mostly a conversation and an exam. The goal is to work out where your pain is actually coming from and what a sensible next step looks like. For many of our patients that pain is in the lower back or running down a leg, which our page on low back pain and sciatica treatment covers in detail. The process below applies whatever brings you in.
Before you arrive
A little preparation makes the visit far more useful. You don’t need a binder of records, but a few things genuinely change what your physician can do in one sitting.
| Bring this | Why it helps |
|---|---|
| Photo ID and insurance card | Needed to register you and check coverage |
| A list of every medication and supplement, with doses | Affects which treatments are safe, especially blood thinners |
| MRI, CT, or X-ray reports, and the images if you have them | Lets your physician compare the scan with your exam rather than reading a summary |
| Notes from past treatment: physical therapy, injections, surgery | What helped, what didn’t, and for how long is real diagnostic information |
| A short list of your questions | First visits move quickly, and it’s easy to forget the thing you most wanted to ask |
Check our accepted insurance list before you come in. Some plans also require a referral from your primary care doctor, so it’s worth a quick call to your insurer if you’re not sure. If you already have an account, the patient portal is the easiest place to keep your information current.
One more thing worth doing: jot down a rough timeline. When did the pain start? Did something set it off? Where does it go, and what makes it better or worse? Five lines on your phone is enough. People tend to remember these details vaguely in the exam room and clearly at home.
The conversation comes first
Expect your physician to spend real time asking questions before examining anything. Where exactly does it hurt? Is it a dull ache, a burning, an electric jolt? Does it travel into a leg or arm? Is it worse in the morning, after sitting, or at the end of the day?
These questions can feel repetitive, especially if you’ve answered them for other doctors. They matter because different pain patterns point to different sources. Pain that shoots below the knee when you cough suggests something different from a deep ache that builds while you sit, a distinction we walk through in sciatica vs. piriformis syndrome.
You’ll also be asked how pain is affecting your life. Be specific. “I can’t sit through a work meeting” or “I stopped walking the dog” tells your physician more than a number on a scale, and it shapes what a realistic goal looks like for you.
The physical exam
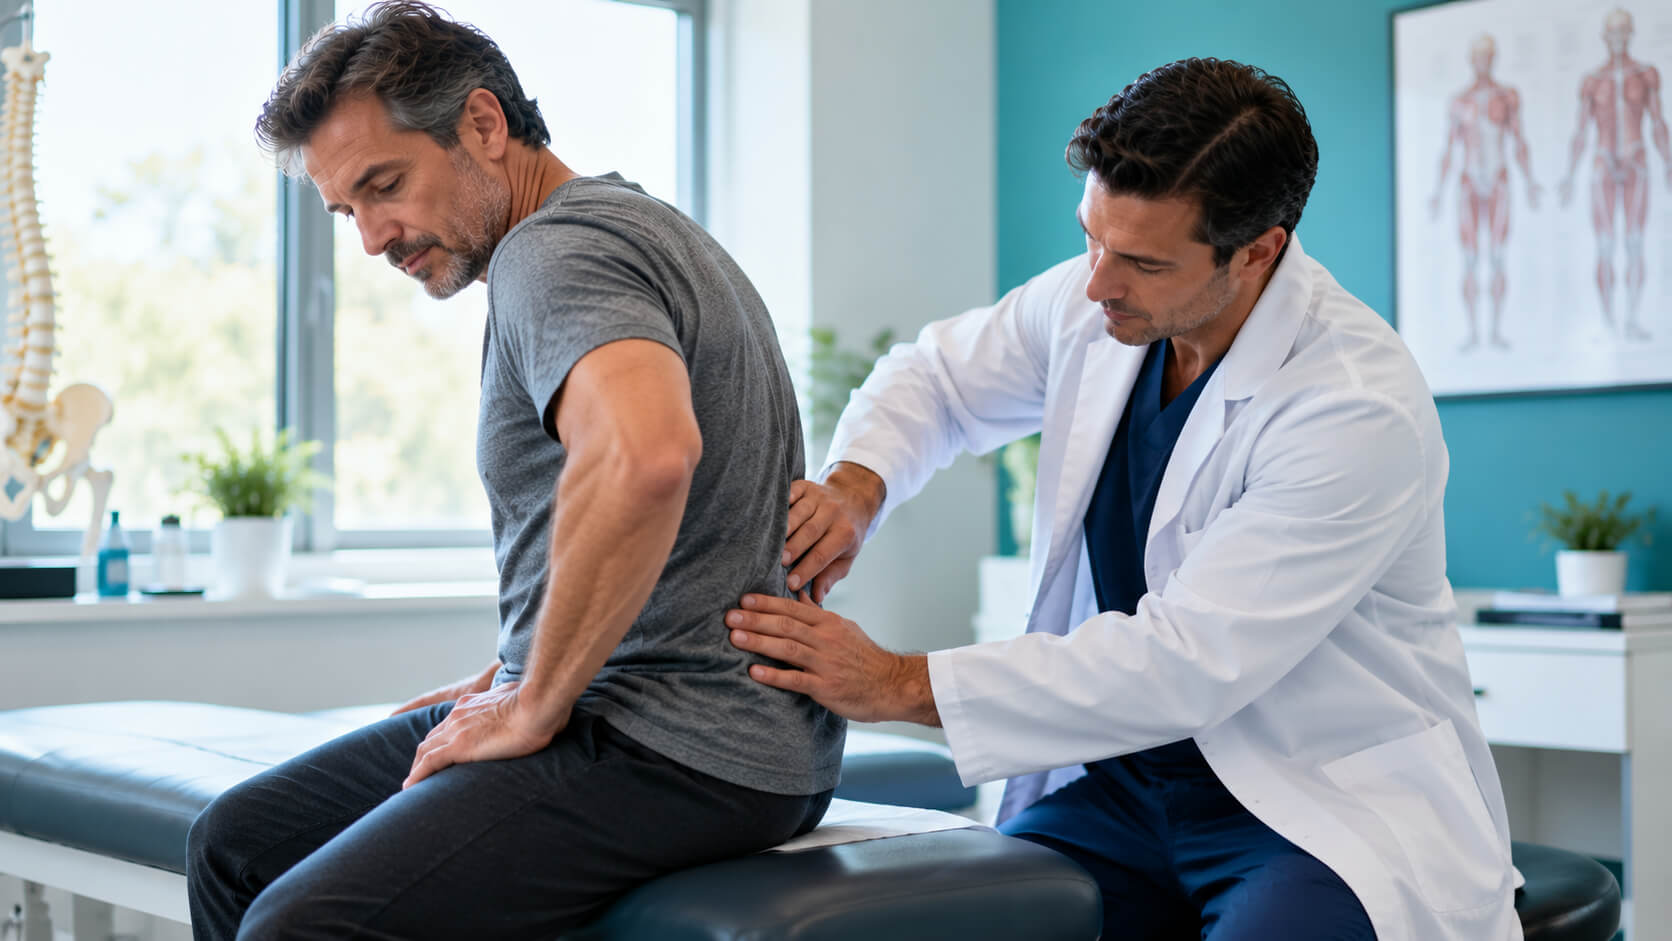
The exam is focused on the area that hurts and the nerves connected to it. Depending on your symptoms, your physician may check your strength, reflexes, and sensation, watch how you walk, and test how your back, hips, or neck move.
Some tests deliberately reproduce your pain for a moment, like raising a straightened leg or pressing on a specific joint. That’s intentional. If a movement recreates your familiar pain, it narrows down where the problem lives. Wear clothing that lets you move comfortably and gives easy access to the painful area.
Will you need new imaging?
Not always. A scan is ordered when it can answer a specific question, not as a routine step. If you already have a recent MRI, your physician will compare it with what the exam shows. That comparison matters because scans often reveal disc bulges and wear in people who have no pain at all, so a finding on paper isn’t automatically the cause.
New imaging becomes more likely if your symptoms have changed since your last scan, if there are signs of nerve weakness, or if a procedure is being planned.
Will you get treatment on day one?
Usually the first visit ends with a plan rather than a procedure. That plan might include physical therapy, a change in medication, further testing, or a targeted procedure such as an epidural steroid injection scheduled for a later date. Procedures typically need their own appointment, and sometimes insurance approval or adjustments to medications like blood thinners first.
If someone recommends an injection before they’ve examined you or reviewed your history, that’s a reasonable moment to ask why. A good plan has a clear target and a clear reason.
Questions worth asking before you leave
You should walk out understanding three things: what your physician thinks is causing the pain, what the next step is, and what you’re hoping it will change. If any of that is fuzzy, ask. A few questions that tend to help:
- What do you think is the most likely source of my pain?
- Does my imaging match what you found on the exam?
- What is this treatment meant to do, and how will we know if it worked?
- What should I do if things get worse before my next visit?
Some symptoms shouldn’t wait for any appointment. Loss of bladder or bowel control, numbness in the groin or inner thighs, or leg weakness that’s quickly getting worse need emergency care right away. Our guide to how long back pain should last before you see a specialist covers the warning signs in more detail.
Booking your first visit
ReclaimAbility Pain Services sees new patients at four South Jersey offices: Mount Laurel, Haddonfield, Washington Township, and Linwood. You can meet our physicians on the Our Team page before you come in.
When you’re ready, request an appointment online or call 855-727-2465, Monday through Friday. Bring your list, bring your questions, and expect to be listened to.
This article is for general education and is not a substitute for a medical evaluation. If you have new or worsening symptoms, talk with a qualified clinician.